
Reflux and Hiatus Hernia
Did You Know?
About one in nine Australian adults (11.6%) have reflux symptoms, such as heartburn or regurgitation, at least once a week.
What Are Reflux and Hiatus Hernia?
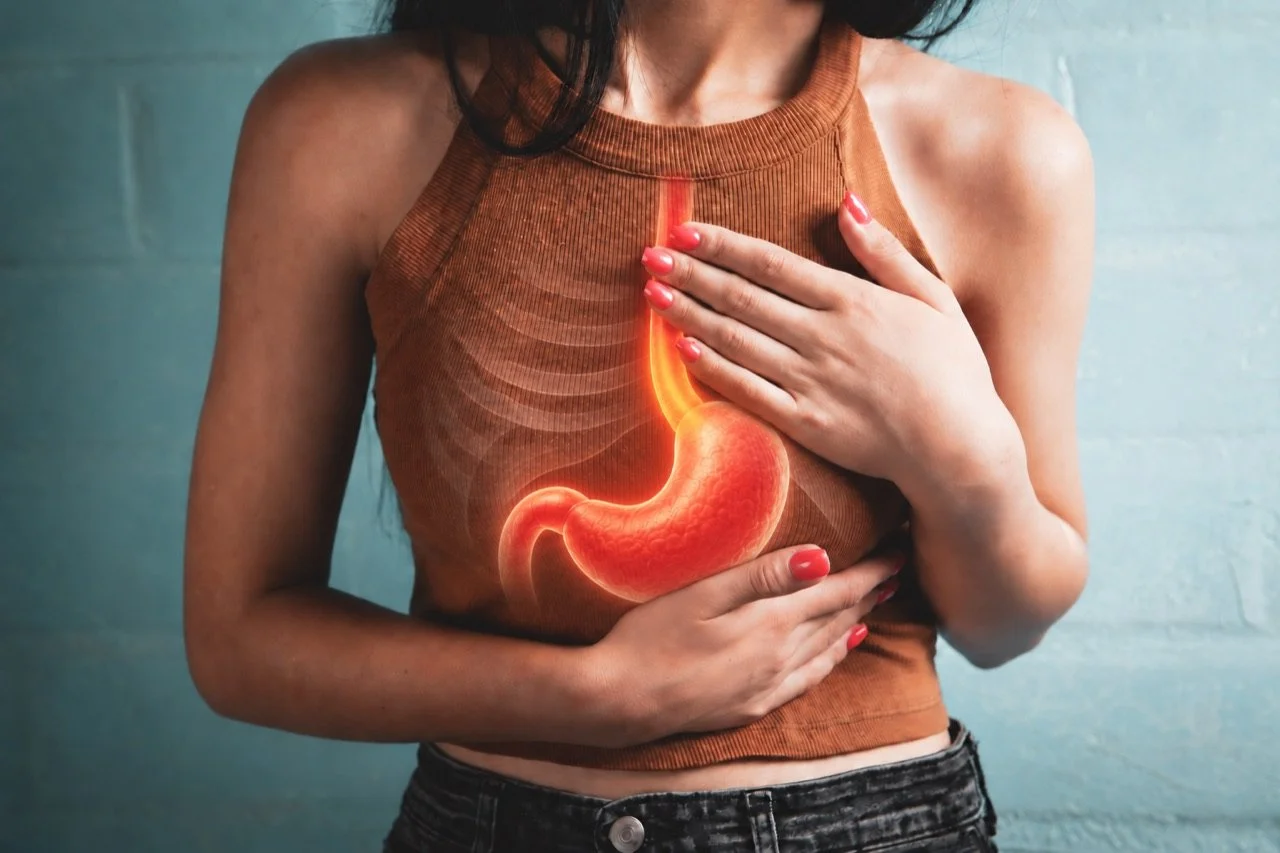
Reflux (gastro-oesophageal reflux disease, or GORD) is when stomach contents come back up into the oesophagus. A hiatus hernia is when part of the stomach slides up through the diaphragm into the chest, which weakens the valve that normally keeps stomach contents where they belong. Large hiatus hernias, sometimes called paraoesophageal hernias, can also cause swallowing problems, volume regurgitation and shortness of breath.


Images adapted from a photo by Sasun Bughdaryan on Unsplash
What Symptoms Does It Cause?
Heartburn, regurgitation, a sour or metallic taste, a cough or hoarse voice, chest discomfort and trouble swallowing (dysphagia). Large hernias can also cause fullness after small meals, breathlessness or anaemia. Reflux can affect your sleep, your eating and your day-to-day comfort, and it can be treated effectively.
When Should I See a Surgeon?
It is worth getting a surgical opinion if:
- your symptoms continue despite medication
- you would rather not take tablets long term
- regurgitation is a problem
- you have a large hiatus hernia
- you have a gastric band and have developed reflux, which can be a sign of a band problem (Lap Band Management)
What Tests Will I Need?
Most people need a gastroscopy, which is done as a day procedure. Some people also need manometry, which measures how the oesophagus squeezes, and pH monitoring, which measures how much stomach acid reaches the oesophagus. Larger hernias may need a barium swallow or CT scan.
What Are the Treatment Options?
Many people do well with lifestyle changes and medication. It is worth knowing, though, that medication doesn't stop reflux: it makes the refluxed fluid less acidic.
If surgery is recommended, it is usually done by keyhole (laparoscopic) surgery. The stomach is returned from the chest to the abdomen, the enlarged gap in the diaphragm is repaired, and the top of the stomach is wrapped around the lower oesophagus (a fundoplication) to rebuild the barrier against reflux. The type of wrap depends on how well your oesophagus works and on your symptoms. If you are also living with obesity, a Roux-en-Y gastric bypass may be an option, and Dr Lourensz will talk through the options with you.
What Are the Benefits and Risks?
The aims of surgery are to repair the hiatus hernia (if present), control reflux, and reduce or stop your need for anti-acid tablets. Risks include trouble swallowing, bloating, the hernia coming back, and the general risks of any operation. Dr Lourensz will go through what is likely in your case at your appointment.
What Happens Next?
Ask your GP for a referral to Dr Lourensz, then request an appointment. We look forward to helping you.
Reviewed by Dr Kaleb Lourensz · Last reviewed October 2026